

Online forums have spread a lot of misinformation about long term use of human chorionic gonadotropin (HCG) losing its effectiveness after weeks of use in men with or without testosterone replacement therapy. But, are those rumors based on actual studies? We will review three studies below. HCG is prescribed as sole therapy in some men to boost their own testosterone production and also in men on testosterone therapy who want to preserve fertility (healthy sperm counts) and testicular size (preventing testicular shrinkage or atrophy).

In clinical reality, HCG is a vital therapeutic tool used for:
Transition: To trace the lineage of this error, we must isolate the specific data point from 1977 that has been stripped of its biological context.
--------------------------------------------------------------------------------
Key Data Points from the Haour Study:
Transition: While the rat data shows a temporary 120-hour recovery cycle under extreme conditions, long-term human clinical observations reveal a consistent pattern of functional durability.
--------------------------------------------------------------------------------
Synthesizing the Smals et al. (1974) Findings The Smals study provides a definitive rebuttal to the idea of HCG "failing." While the researchers observed that testosterone levels in Klinefelter patients tended to decrease slightly from their initial treatment peak as therapy continued, the levels remained higher than pre-treatment values. This indicates that the Leydig cells were not becoming "exhausted" but were reaching a new, elevated steady state. Even in Klinefelter patients—who have compromised testicular function—the "functional reserve" was maintained over the long term.
Transition: These clinical findings provide the foundation for why modern medical experts view the desensitization theory as a fundamental misunderstanding of biological feedback loops.
--------------------------------------------------------------------------------
Transition: For the aspiring learner, these findings clarify the distinction between short-term receptor occupancy and long-term testicular health.
--------------------------------------------------------------------------------
The Use of HCG in Men
This Study Of Two People Did not Show Issues After 23 Months of High Doses:
A STUDY OF HUMAN TESTICULAR FUNCTION BY THE USE OF HUMAN MENOPAUSAL GONADOTROPHIN AND OF HUMAN CHORIONIC GONADOTROPHIN IN MALE HYPOGONADOTROPHIC EUNUCHOIDISM AND INFANTILISM in: European Journal of Endocrinology Volume 53 Issue 2 (1966)
Abstract

Two adult men with severe hypogonadotrophic hypogonadism (persisting infantilism) were observed during long-term treatment with chorionic gonadotrophin (HCG) (23 and 6 months respectively) followed by treatment with human menopausal gonadotrophin (HMG) (for 7 and 12 months) and finally by combined treatment with
HMG plus HCG (for 12 and 9 months). A study of hormone excretion, testicular biopsies and the clinical course showed that HMG given alone had little effect. Development of the testicular tubules was dependent upon the addition of HCG to the HMG, and the combined treatment induced a complete gonadal maturation. This LH action is presumably a direct effect on the tubules rather than indirect through Leydig cell stimulation. HMG acts synergistically with HCG in Leydig cell stimulation, and the results thus indicate a close interaction between FSH and LH on all testicular elements. No lasting effect of the long-term treatment was found. HMG has no antigenic properties in the human.
This Additional Study Showed no Long Term Reduction in Efficacy:
Smals et al. THE EFFECT OF SHORT AND LONG TERM HUMAN CHORIONIC GONADOTROPHIN (HCG) ADMINISTRATION ON PLASMA TESTOSTERONE LEVELS IN KLINEFELTER’S SYNDROME European Journal of Endocrinology, Dec 1974. Page(s): 753–764Volume/Issue: Volume 77: Issue 4
The effect of acute (1500 IU/day for 3 days) and chronic HCG administration (1500 IU, 3 times weekly) on plasma In all but one Klinefelter patient the plasma LH levels were markedly elevated even in the presence of normal testosterone levels. No significant correlation could be demonstrated between the plasma testosterone concentrations and the LH levels in the Klinefelter patients. Short term HCG administration resulted in a significant increase in the plasma testosterone levels in each of the 3 groups studied, independent of the basal value. The absolute increase in the Klinefelter patients was quantitatively comparable to that in the patients with secondary hypogonadism, but significantly lower than in the eugonadal controls. During long term HCG treatment the plasma testosterone levels definitely increased in both patient groups, but remarkably in the Klinefelter patients testosterone levels tended to decrease on continuing treatment, though in most patients testosterone levels remained higher than the pre-treatment values. The data on the effect of acute and chronic HCG administration on plasma testosterone levels in this study illustrate again that Leydig cells in Klinefelter’s syndrome still retain a functional reserve, though less than in eugonadal males.
This old study in rats probably fueled the misconception popular in other online forums about HCG desensitization, but at this relatively high dose in rat cells (IU/Kg), HCG receptor occupancy returned to normal after 120 hours. How can we extrapolate to humans?
Haour et al, HCG-Dependent Regulation of Gonadotropin Receptor Sites:
Negative control in testicular leydig cells. Molecular and Cellular Endocrinology, Volume 7, Issue 1, March 1977, Pages 17-24
Abstract
https://www.excelmale.com/video-how...-preserve-fertility-libido-and-testicle-size/
A single injection of human chorionic gonadotropin (hCG 500 IU) to prepubertal male rats increases plasma testosterone level and decreases hCG receptors in the testicular Leydig cells for more than 120 h. Injected hCG, measured in plasma using a specific radioreceptor assay for gonadotropins, is maximal at 2 h and decreases thereafter with an apparent half-life of 16 h. Plasma testosterone exhibits a rapid increase (30–40 ng/ml) within 1 h after hCG injection. A delayed paradoxical increase (20–30 ng/ml) is observed between 48 and 120 h after the injection. The number of hCG binding sites in the isolated Leydig cells membranes decreases to less than 10% of the control value within 10 h and remains almost undetectable until 96 h after hCG injection. The reappearance of the binding sites is observed around 120 h. Similar, but less pronounced effects are found after the injection of 10 IU hCG. Since receptor occupancy cannot explain such a phenomenon, it is concluded that hCG is exerting a negative control on its own receptors in the Leydig cells.
Video: How to Use hCG
Evidence Fact Sheet: HCG and the Leydig Cell Desensitization Myth
1. Introduction: The "Desensitization" Claim vs. Clinical Reality
In the realm of androgen replacement, a persistent myth suggests that Human Chorionic Gonadotropin (HCG) is a double-edged sword. Online "authorities" frequently warn that long-term HCG use will eventually "fry" the Leydig cells, leading to a permanent state of desensitization where the testes no longer respond to luteinizing hormone (LH) signals. This fear-based narrative often leads patients to unnecessarily cycle the medication or avoid it altogether.In clinical reality, HCG is a vital therapeutic tool used for:
- Intratesticular Testosterone Preservation: Maintaining natural production during TRT.
- Fertility Maintenance: Supporting spermatogenesis by mimicking LH.
- Prevention of Testicular Atrophy: Maintaining organ volume and cellular activity.
Transition: To trace the lineage of this error, we must isolate the specific data point from 1977 that has been stripped of its biological context.
--------------------------------------------------------------------------------
2. Deconstructing the Origin: The 1977 Haour et al. Rat Study
The primary source of the desensitization myth is a 1977 study titled "hCG-Dependent regulation of gonadotropin receptor sites." While the study provided valuable insights into receptor dynamics, its findings have been grossly misinterpreted by the lay public.Key Data Points from the Haour Study:
- The Subject: The researchers used prepubertal male rats, whose endocrine systems are in a state of rapid development and are not biologically identical to adult human males.
- The Immediate Effect: Following a single injection of 500 IU of HCG, binding sites in the Leydig cell membranes decreased to less than 10% of control values within 10 hours.
- The "120-Hour Recovery": Crucially, this was not permanent. Binding sites returned to normal levels by approximately 120 hours post-injection.
- The "Paradoxical Increase": Despite the low receptor count, a secondary spike in testosterone (20–30 ng/ml) occurred between 48 and 120 hours, proving the cells remained functionally responsive even with reduced receptor density.
Transition: While the rat data shows a temporary 120-hour recovery cycle under extreme conditions, long-term human clinical observations reveal a consistent pattern of functional durability.
--------------------------------------------------------------------------------
3. Evidence from Human Clinical Trials: Long-Term Outcomes
When we move from rodents to humans, the "desensitization" theory collapses under the weight of long-term longitudinal data.| Title/Year | Patient Profile | Duration & Dosage | Key Findings regarding Desensitization |
| A Study of Human Testicular Function... (1966) | Two adult men with severe hypogonadotrophic hypogonadism (persisting infantilism). | One patient for 23 months; one for 6 months. High-dose HCG, later HMG/HCG combo. | HMG alone had little effect. Complete gonadal maturation required the addition of HCG. Long-term treatment produced no lasting negative effects or loss of Leydig cell function. |
| The Effect of Short and Long Term HCG Administration... (1974) | Klinefelter’s syndrome patients and secondary hypogonadism patients. | Chronic administration: 1500 IU, 3 times weekly. | Leydig cells in Klinefelter patients retained a functional reserve. Levels remained significantly higher than pre-treatment baselines throughout the study. |
Synthesizing the Smals et al. (1974) Findings The Smals study provides a definitive rebuttal to the idea of HCG "failing." While the researchers observed that testosterone levels in Klinefelter patients tended to decrease slightly from their initial treatment peak as therapy continued, the levels remained higher than pre-treatment values. This indicates that the Leydig cells were not becoming "exhausted" but were reaching a new, elevated steady state. Even in Klinefelter patients—who have compromised testicular function—the "functional reserve" was maintained over the long term.
Transition: These clinical findings provide the foundation for why modern medical experts view the desensitization theory as a fundamental misunderstanding of biological feedback loops.
--------------------------------------------------------------------------------
4. Synthesis: Why the Myth Persists vs. What the Evidence Says
The "desensitization" theory is considered flawed by experts for three primary reasons:- Dose and Species Disparity: There is no clinical basis for applying a 1,666 IU/kg rat dose to human TRT protocols. Human doses are orders of magnitude lower and do not trigger the extreme down-regulation seen in animal models.
- The 120-Hour Receptor Recovery: Critics of HCG mistake "temporary downregulation" for "permanent desensitization." Think of this as a biological thermostat: the system temporarily turns down the "heat" (receptors) when there is an abundance of signal, but the machine is not broken. Receptors cycle back to normal within days.
- Human Clinical Longevity: Studies spanning 23+ months demonstrate that Leydig cells continue to mature and function without "burning out," even at dosages higher than those typically used in modern TRT.
Transition: For the aspiring learner, these findings clarify the distinction between short-term receptor occupancy and long-term testicular health.
--------------------------------------------------------------------------------
5. Final Takeaways for the Aspiring Learner
When evaluating HCG myths, keep these three insights at the forefront of your clinical reasoning:- Down-regulation is Not Damage: A temporary decrease in HCG receptors is a homeostatic adjustment, not cellular destruction. The Leydig cell is a resilient organ, not a fuse that "blows" when stimulated.
- Contextualize the Research: If a claim of "desensitization" relies on rat studies, calculate the IU/kg dose. You will likely find the dose is 500x higher than what is used in human medicine.
- The Baseline Safety Net: Evidence shows that most men who discontinue HCG and testosterone return to their pre-treatment baseline without lasting negative effects. In many cases, HCG use during TRT makes the recovery of natural function easier by keeping the Leydig cells in a functional, "ready" state compared to the profound atrophy seen with testosterone-only protocols.
The Use of HCG in Men
This Study Of Two People Did not Show Issues After 23 Months of High Doses:
A STUDY OF HUMAN TESTICULAR FUNCTION BY THE USE OF HUMAN MENOPAUSAL GONADOTROPHIN AND OF HUMAN CHORIONIC GONADOTROPHIN IN MALE HYPOGONADOTROPHIC EUNUCHOIDISM AND INFANTILISM in: European Journal of Endocrinology Volume 53 Issue 2 (1966)
Abstract
Two adult men with severe hypogonadotrophic hypogonadism (persisting infantilism) were observed during long-term treatment with chorionic gonadotrophin (HCG) (23 and 6 months respectively) followed by treatment with human menopausal gonadotrophin (HMG) (for 7 and 12 months) and finally by combined treatment with
HMG plus HCG (for 12 and 9 months). A study of hormone excretion, testicular biopsies and the clinical course showed that HMG given alone had little effect. Development of the testicular tubules was dependent upon the addition of HCG to the HMG, and the combined treatment induced a complete gonadal maturation. This LH action is presumably a direct effect on the tubules rather than indirect through Leydig cell stimulation. HMG acts synergistically with HCG in Leydig cell stimulation, and the results thus indicate a close interaction between FSH and LH on all testicular elements. No lasting effect of the long-term treatment was found. HMG has no antigenic properties in the human.
This Additional Study Showed no Long Term Reduction in Efficacy:
Smals et al. THE EFFECT OF SHORT AND LONG TERM HUMAN CHORIONIC GONADOTROPHIN (HCG) ADMINISTRATION ON PLASMA TESTOSTERONE LEVELS IN KLINEFELTER’S SYNDROME European Journal of Endocrinology, Dec 1974. Page(s): 753–764Volume/Issue: Volume 77: Issue 4
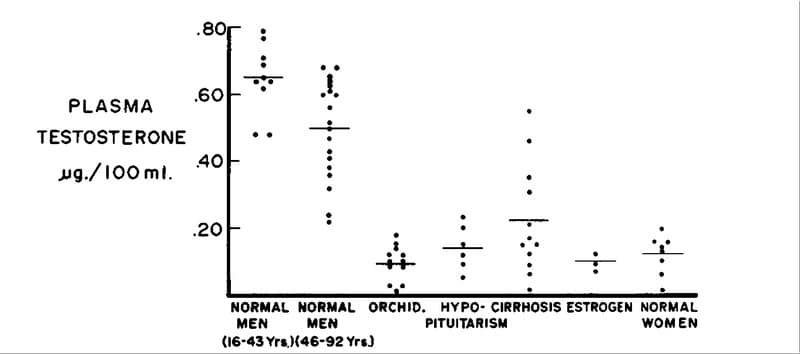
The effect of acute (1500 IU/day for 3 days) and chronic HCG administration (1500 IU, 3 times weekly) on plasma In all but one Klinefelter patient the plasma LH levels were markedly elevated even in the presence of normal testosterone levels. No significant correlation could be demonstrated between the plasma testosterone concentrations and the LH levels in the Klinefelter patients. Short term HCG administration resulted in a significant increase in the plasma testosterone levels in each of the 3 groups studied, independent of the basal value. The absolute increase in the Klinefelter patients was quantitatively comparable to that in the patients with secondary hypogonadism, but significantly lower than in the eugonadal controls. During long term HCG treatment the plasma testosterone levels definitely increased in both patient groups, but remarkably in the Klinefelter patients testosterone levels tended to decrease on continuing treatment, though in most patients testosterone levels remained higher than the pre-treatment values. The data on the effect of acute and chronic HCG administration on plasma testosterone levels in this study illustrate again that Leydig cells in Klinefelter’s syndrome still retain a functional reserve, though less than in eugonadal males.
This old study in rats probably fueled the misconception popular in other online forums about HCG desensitization, but at this relatively high dose in rat cells (IU/Kg), HCG receptor occupancy returned to normal after 120 hours. How can we extrapolate to humans?
Haour et al, HCG-Dependent Regulation of Gonadotropin Receptor Sites:
Negative control in testicular leydig cells. Molecular and Cellular Endocrinology, Volume 7, Issue 1, March 1977, Pages 17-24
Abstract
https://www.excelmale.com/video-how...-preserve-fertility-libido-and-testicle-size/
A single injection of human chorionic gonadotropin (hCG 500 IU) to prepubertal male rats increases plasma testosterone level and decreases hCG receptors in the testicular Leydig cells for more than 120 h. Injected hCG, measured in plasma using a specific radioreceptor assay for gonadotropins, is maximal at 2 h and decreases thereafter with an apparent half-life of 16 h. Plasma testosterone exhibits a rapid increase (30–40 ng/ml) within 1 h after hCG injection. A delayed paradoxical increase (20–30 ng/ml) is observed between 48 and 120 h after the injection. The number of hCG binding sites in the isolated Leydig cells membranes decreases to less than 10% of the control value within 10 h and remains almost undetectable until 96 h after hCG injection. The reappearance of the binding sites is observed around 120 h. Similar, but less pronounced effects are found after the injection of 10 IU hCG. Since receptor occupancy cannot explain such a phenomenon, it is concluded that hCG is exerting a negative control on its own receptors in the Leydig cells.
Video: How to Use hCG
Last edited:

















